NAD+ molecule and dinucleotide — nuupeptide
The small molecule comes first. Once its chemistry is clear, the precursor trials and the heart experiment become much easier to place.
Nicotinamide adenine dinucleotide
The full name is nicotinamide adenine dinucleotide. Dinucleotide means two nucleotides joined together: nicotinamide mononucleotide and adenosine monophosphate, linked by bridging phosphate groups. The formula is C21H27N7O14P2. NAD+ is a coenzyme, a helper molecule used by enzymes, with a central role in energy metabolism and cellular signaling.
Its nicotinamide ring accepts a hydride ion as NAD+ becomes NADH; NADH can then donate electrons. These exchanges connect the breakdown of food with the mitochondrial machinery that makes ATP. Calling it an energy molecule is understandable, though I picture a molecule repeatedly participating in reactions.
NAD+ has a second sort of work. Sirtuins, PARPs and CD38 consume it during their reactions. The distinction between cycling and consumption explains why a cell needs both a usable pool and ways to rebuild that pool.
How is NAD+ made?
Cells have several biosynthetic routes to NAD+. They can begin with tryptophan, with nicotinic acid, or with material recovered through the salvage pathway. Salvage is a useful name: nicotinamide released when NAD+ is consumed can go back into production.
In that recycling route, NAMPT converts nicotinamide to NMN. NAMPT is the rate-limiting enzyme, so its activity constrains this part of the supply. NMN is then converted to NAD+. Nicotinamide riboside, or NR, enters through conversion to NMN.
That is why the substances in the oral trials deserve their full names. NMN and NR are precursors from which cells build NAD+. Intact NAD+ is poorly transported into most cells. I distrust summaries that silently swap a precursor for the finished dinucleotide; it makes the trial sound as though it tested a different substance.
Is NAD+ a substrate or product?
Both descriptions can be correct. NAD+ is a product of its biosynthetic reactions. It serves as a substrate when an enzyme uses it in a reaction, including the NAD+-consuming reactions of sirtuins, PARPs and CD38. In redox reactions, NAD+ accepts electrons and becomes NADH; the partner reaction can regenerate NAD+. The particular reaction determines the answer.
Consumption also connects the molecule to aging research. In the 2016 mouse experiments involving CD38, mice without that enzyme retained NAD+ and SIRT3 activity and had better mitochondrial and metabolic function with age. That genetic experiment makes consumption a concrete part of the biology. The human picture needs its own measurements: the 2025 clinical review found that a consistent age-related decline had been observed in only a limited number of human studies.
Whole-blood NAD+ in the NR trial
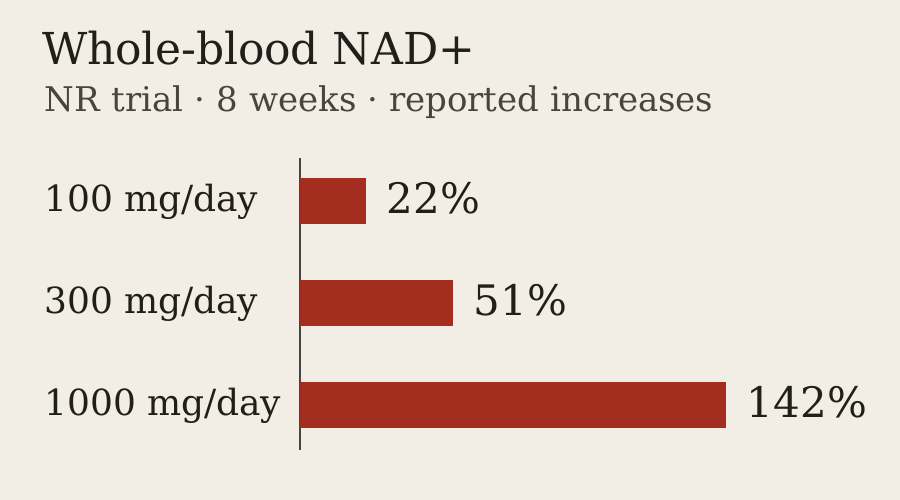
The 2019 placebo-controlled NR trial in healthy overweight adults has an unusually clear measurement to display. The trial covered oral NR amounts from 100–1000 mg/day over 8 weeks. Whole-blood NAD+ rose by 22%, 51% and 142% at the three study amounts shown below. These are the study’s administered amounts and reported results.
No flushing was reported, and adverse events did not differ significantly from placebo at any tested amount. NR did not elevate LDL cholesterol or disrupt one-carbon metabolism.
I like how legible this result is. The measured blood pool moved. The separate question of how much NAD+ reached a particular tissue, and what that tissue then did, remains open. The bars below show the blood result alone.
Two NMN trials
In prediabetic, postmenopausal women studied for 10 weeks, oral NMN at 250 mg/day improved muscle insulin sensitivity, assessed with a hyperinsulinemic-euglycemic clamp. The technique measures insulin’s effect on glucose handling under controlled conditions. Muscle insulin signaling changed, while body composition and HbA1c did not.
A multicenter trial in middle-aged adults tested oral NMN over the 300–900 mg/day range for 60 days. Blood NAD+ increased at days 30 and 60 across all NMN groups compared with placebo (p≤0.001). The trial also reported improved walking distance and quality-of-life scores, with no safety issues at the amounts studied.
Those results earn space here. So does the 2025 review’s conclusion of limited human efficacy. A favorable trial can sit comfortably beside a cautious synthesis when the population, substance and measured outcome remain visible.

Cardiac tissue and HMGCS2
The heart’s intrinsic ketone-making capacity is the finding that brought me back to this molecule. The work combined human myocardium with a mouse model of heart failure with preserved ejection fraction. In the mouse model, NAD+ repletion restored HMGCS2 activity through deacetylation, increased fatty acid oxidation and rescued cardiac function; reducing HMGCS2 in cardiomyocytes prevented that rescue.
This gets a prominent place in my exhibition of newly noticed capabilities of familiar tissue. The specificity is the attraction. HMGCS2 mattered to the effect, and the functional rescue was an animal finding. A trial of human treatment would have to establish its own outcomes.
Oral tolerability; infusion risks
The short oral trials provide tolerability information for particular precursors, participants and durations. They leave long-term safety questions open. NAD+ biology in disease also makes cancer a difficult context: supporting the metabolism of existing cancer cells is a theoretical concern, and its roles in oncology depend on the setting.
IV NAD+ carries separate concerns. The existing clinical literature is limited; rapid infusion can cause chest or abdominal discomfort, flushing and nausea. FDA recalled a compounded NAD+ injection over elevated bacterial endotoxin. Its designation was Class I. Those preparation and route risks cannot be answered by an oral precursor trial.
NAD+ and its precursors are marketed as supplements. FDA has challenged NMN’s supplement status because of its investigation as a drug. Compounded injectable NAD+ has no FDA approval. NAD+ and its precursors are not prohibited by WADA. Supplement purity and actual content can vary. Personal treatment decisions need clinical assessment; this page supplies no regimen.